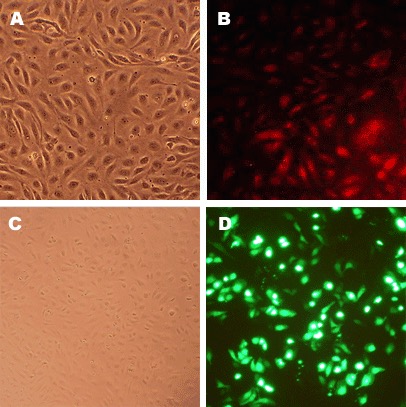
Human Coronary Artery Endothelial Cells: HCAEC (A). HCAEC stained with DiI-Ac-LDL, the acetylated apoprotein specifically recognized & endocytosed by endothelial cells (B). HCAEC transfected with GFP plasmid DNA using Cytofect™ Endothelial Cell Transfection Kit (C&D).
Human Coronary Artery Endothelial Cells: Plaque: HCAEC-q
Human Coronary Artery Endothelial Cells-Plaque (HCAEC-q) are primary macrovascular cells isolated from the human coronary arteries at the site of atheromatous plaque formations.
Description
Human Coronary Artery Endothelial Cells-Plaque (HCAEC-q) are primary macrovascular cells isolated from the human coronary arteries at the site of atheromatous plaque formations. These cells, which are also referred to as plaque-associated HCAEC cells, exhibit characteristic cell morphology and positive expression of pan-endothelial markers such as CD31 and vWF factor VIII. Unlike healthy cells, HCAEC-q are often studied to understand their distinct epigenetic signatures and chronic signaling phenotypes, which are shaped by the fibroatheroma microenvironment. By maintaining these cells in specialized Meso Endo Growth medium, researchers can investigate their roles in coronary artery disease and their contribution to plaque vulnerability.
The pathogenesis of atherosclerotic plaques involves a complex, localized inflammatory response that distinguishes the endothelium covering a lesion from the surrounding healthy vessel wall.
- Endothelial-to-Mesenchymal Transition (EndMT): A critical feature of plaque-associated cells is their potential to undergo EndMT, a process in which they lose classical endothelial markers (e.g., CD31) and acquire mesenchymal traits (e.g., α-SMA expression). This transition contributes significantly to plaque fibrosis and structural instability.
- Endothelium Dysfunction: HCAEC-q cells often display a baseline upregulation of cellular adhesion molecules (e.g., VCAM-1, ICAM-1), facilitating the recruitment of immune cells. This dysfunction, characterized by impaired nitric oxide bioavailability and oxidative stress, contributes to the overall progression of cardiovascular diseases.
- Mechanical and Biomechanical Stress: These cells are utilized to study how plaque-associated regions suppress anti-atherogenic pathways, often leading to localized vasoconstriction and a pro-thrombotic state that elevates the risk of thrombosis.
A defining feature of vulnerable plaques—which are characterized by a thin fibrous cap, a large lipid core, and high inflammatory cell content, making them prone to rupture and subsequent thrombosis—is intra-plaque neovascularization, which researchers monitor through specific vessel growth patterns in in vitro models.
- Hypoxia and Angiogenesis: In the hypoxic core of a fibroatheroma, these cells respond to growth factor gradients; however, they often form immature and permeable capillaries that contribute to plaque hemorrhage.
- Complex Interactions: The stability of the plaque is also determined by cross-talk between the HCAEC-q cells and neighboring smooth muscle cells within the lesion. Research into this cross-talk often involves sophisticated techniques to assess differential N-glycosylation profiles, which may influence the structural integrity of the vessel.
HCAEC-q cells provide a rigorous human platform for validating novel disease treatments aimed at protecting the vasculature.
- Therapeutic Validation: Researchers use these models to test compounds that mitigate inflammation or stabilize the endothelium. Specific interventions, such as HCAEC BMP-4 treatment, are frequently used to probe these response pathways; BMP-4 acts as a pro-atherogenic factor that induces oxidative stress and exacerbates endothelial dysfunction in plaque-associated cells.
- Modeling Cardiovascular Outcomes: By integrating these cells into microfluidic or organ-on-a-chip platforms, researchers can simulate the effects of disturbed blood flow on coronary blood flow and cardiac function. These advanced models are critical for predicting how plaque physiology impacts the overall severity of coronary heart disease and the potential for clinical events.
- Quality Control: To ensure data integrity, researchers monitor for contaminants such as mycoplasma that could affect the accuracy of these sensitive vascular models.
Human Coronary Artery Endothelial Cells (HCAEC) from Cell Applications, Inc. provide an excellent model system to study all aspects of cardiovascular function and disease, and they have been utilized in dozens of research publications, for example to:
- Understand the mechanism of the anti-inflammatory properties of HDL, and demonstrate for the first time that mature miRNA can control gene expression in a cell where it is neither transcribed nor processed
- Study mechanisms of angiogenesis, as well as oxidative stress and inflammation related pathways in endothelia, including gender and race specific differences in patients with peripheral artery disease
- Elucidate molecular mechanisms of various cardiovascular risk factors, including those associated with diabetes
- Understand the mode of action and cardiovascular protection effects of various natural compounds, vitamins and drug candidates
- Develop and evaluate scaffolds and hydrogels for cardiac tissue engineering, and new treatment strategies to prevent stent restenosis
- Compare effects of BMP-4 on HCAEC and Human Pulmonary Artery Endothelial Cells (HPAEC, also from Cell Applications, Inc.)
- Show that only in HCAEC BMP-4 treatment induced ROS, activated NF-kB, ICAM-1 and increased monocyte adhesiveness, explaining why its upregulation leads to atherosclerosis and hypertension in the systemic, but not pulmonary circulation
Additionally, HCAEC, along with human aortic (HAOEC), carotid artery (HCtAEC), subclavian artery (HScAEC) and brachiocephalic artery (HBcAEC), all provided by Cell Applications, Inc., have been used to demonstrate that not only blood vessels from different tissues are highly heterogeneous, they also interact differently with leukocytes during the inflammation response. The authors further showed that differential N-glycosylation of commonly expressed vascular adhesion molecules may be responsible for this heterogeneity, as well as for modulation of signaling under resting and activated inflammatory conditions. This also explains why specific vascular beds may be more or less susceptible to particular diseases or stimuli. Importantly, if cells from different sources were used, these results could not be convincingly validated due to a number of uncontrolled variables, such as age, race, genetic variability or life style choices of the donors. To eliminate the donor-to-donor variability, the scientists took advantage of the great variety of primary cells offered by Cell Applications, including the option of ordering a panel of endothelial cells obtained from different vascular beds of the same donor!
Because of the complex heterogeneity that exists not only between different donors, but even between different vascular beds in the same individual, it would be prudent to confirm any new findings on primary cell lots coming from several different origins.
Details
| Tissue | Normal healthy human coronary artery | |
|---|---|---|
| QC | No bacteria, yeast, fungi, mycoplasma, virus | |
| Character | Factor VIII-related Ag, DiI-Ac-LDL uptake | |
| Bioassay | Attach, spread, proliferate in Growth Med | |
| Cryovial | 500,000 HCAEC-q (2nd passage) frozen in Basal Medium w/ 10% FBS, 10% DMSO | |
| Kit | Cryovial frozen HCAEC-q (300q-05a), Growth Med (212-500), Subculture Rgnt Kit (090K) | |
| Proliferating | Shipped in Gr Med, 3rd psg (flasks or plates) | |
| Doublings | At least 15 | |
| Applications | Laboratory research use only (RUO). Not for human, clinical, diagnostic or veterinary use. |
Resources
FAQs
Need More Help?
Visit our comprehensive FAQ page for detailed answers to common questions.
Need More Help?
Visit our comprehensive FAQ page for detailed answers to common questions.
Primary Cell FAQs Powered by Bioz